Choosing a knee replacement surgeon requires more than searching for the words “best” or “advanced.” You need to confirm that surgery is appropriate, understand which replacement fits your knee, verify the surgeon’s training and experience, and compare evidence about safety, recovery, and long-term function.
Key takeaways
- Confirm non-surgical treatment has failed before choosing a surgeon.
- Ask how imaging, symptoms, function, and medical history establish candidacy.
- Match the surgeon’s experience to your likely knee replacement procedure.
- Compare complication rates, rehabilitation plans, and follow-up systems—not marketing claims.
Confirm That Surgery Is the Right Next Step
A knee replacement consultation makes sense when diagnosed arthritis continues to cause substantial pain or stiffness despite a well-run non-surgical plan, and the problem limits walking, stairs, sleep, work, or personal care. Seek assessment sooner when deformity is worsening, pain occurs at rest, or knee function is shrinking rapidly.
- Ask whether you have completed an appropriate trial of physiotherapy, home exercise, activity modification, and weight management when relevant.
- Review whether anti-inflammatory medicines and injections were safe, properly selected, and genuinely ineffective. Do not continue a treatment that causes stomach bleeding, kidney problems, uncontrolled blood pressure, or other serious effects.
- Bring a record of pain, walking distance, sleep disruption, work limitations, and treatments tried. These details help distinguish tolerable symptoms from disability that justifies surgery.
A consultation does not commit you to an operation. The surgeon should explain why replacement is preferable to continued care, what pain and function it is likely to improve, and what it will not fix; kneeling, squatting, stiffness, clicking, and activity limits can remain.
Ask how the surgeon manages revision knee replacement, including referral for bone loss or infection, because a clear pathway matters even before a primary operation.
Check How the Surgeon Confirms Your Candidacy
A recommendation for knee replacement should combine your symptoms, examination, and weight-bearing imaging—not an X-ray alone. The surgeon should connect the scan findings with pain and daily activities, including walking distance, stairs, sleep, work, and whether non-surgical treatment has stopped providing useful relief.
1. Expect a focused history and physical examination. The surgeon should assess gait, knee range of motion, swelling, tenderness, ligament stability, leg deformity, muscle strength, and circulation. They should also consider hip or spine problems that can mimic knee pain.
Ask how these findings support replacement rather than continued physiotherapy, medicines, injections, weight management, or activity modification.
2. Ask to review standing knee X-rays. Weight-bearing anteroposterior, lateral, and patellofemoral views show joint-space loss, bone changes, deformity, and arthritis severity under load. A non-weight-bearing image can make the joint look less damaged than it behaves when you stand.
3. Confirm whether long-leg alignment films are needed. These images show the hip-to-ankle mechanical axis and help plan correction of bow-legged or knock-kneed alignment.
4. Treat MRI for knee replacement as a selective test, not an automatic requirement. MRI helps when X-rays do not explain symptoms, a ligament or cartilage problem is suspected, or another diagnosis needs investigation. If infection, inflammatory arthritis, or a previous operation raises concern, ask whether blood tests or joint-fluid analysis are necessary before surgery.
Match the Surgeon’s Expertise to the Operation You May Need
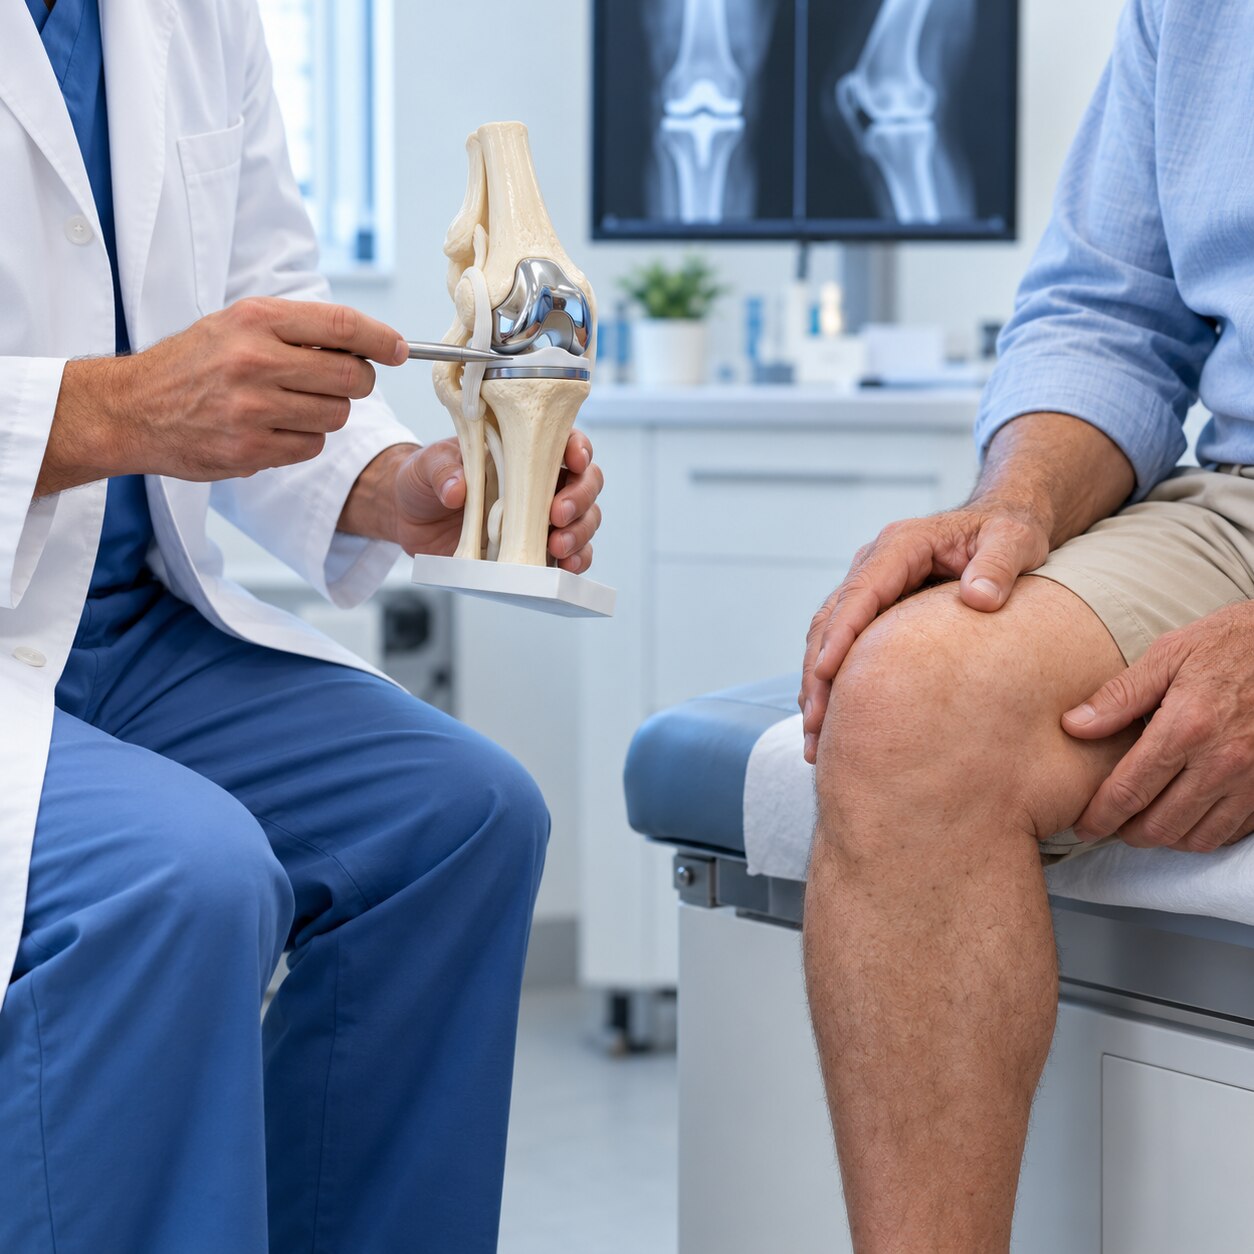
The operation you may need should guide your surgeon choice. Total knee replacement resurfaces the damaged surfaces across the knee, while partial or unicompartmental knee replacement treats disease confined to one compartment. Revision knee replacement replaces or repairs components from an earlier operation and demands different expertise.
| Option | What it means | When it applies |
|---|---|---|
| Total knee replacement | Replaces the femoral and tibial joint surfaces, often with the kneecap surface | Arthritis affects multiple compartments, or a partial replacement would not provide durable correction |
| Partial or unicompartmental knee replacement | Resurfaces one compartment while preserving more native bone, cartilage, and ligaments | Disease is limited to one compartment and the remaining knee structures, alignment, and ligament function meet strict criteria |
| Revision knee replacement | Removes or replaces loose, worn, infected, or failed components and manages bone loss | Pain, loosening, instability, infection, fracture, or another failure follows previous replacement |
Ask for the surgeon’s personal annual numbers for primary and revision knee replacements, not only the hospital’s total. A revision specialist should explain implant options, bone-loss management, and staged treatment for infection; if they do not perform revisions, request a named referral pathway.
Verify these qualifications independently:
- Board certification and professional registration with the relevant national or state authority; in the United States, check the American Board of Orthopaedic Surgery or ABMS Certification Matters.
- Fellowship training in adult reconstruction or knee surgery, with the fellowship institution and dates.
- Surgeon-specific complication, infection, and revision results, interpreted alongside patient risk and case complexity.
Board certification confirms training and examinations, not superior outcomes or high current volume.
Ask About Technique, Implants, Risks, and Recovery
Ask for the reason behind every recommendation, not just the brand name. A suitable implant type depends on your bone quality, ligament stability, age, activity goals, allergies, and whether this is primary or revision surgery.
- “Why is this implant right for my knee, and what alternatives did you reject?”
- “Which surgical approach will you use, and how could it affect pain, muscle damage, movement, or later revision?”
- “What fixation method will you use: cemented, cementless, or hybrid, and why does it suit my bone?”
- “Will you use robotic-assisted knee replacement? If so, what problem will it solve in my case?” Robotics can improve component-position consistency, but it has not consistently produced better pain, function, complication, or long-term-survival results than well-performed conventional surgery.
| Decision | Ask for | Why it matters |
|---|---|---|
| Implant type | The design, materials, expected lifespan, and backup option | A fashionable brand is not automatically the best match |
| Surgical approach | The incision and structures preserved or divided | Technique affects rehabilitation demands |
| Fixation method | Why cemented, cementless, or hybrid fixation fits your bone | Poor fixation can cause loosening or prolonged recovery |
| Recovery plan | Walking milestones, physiotherapy schedule, driving limits, and work restrictions | Vague timelines make setbacks harder to identify |
Ask for the exact pain medicines, blood-clot-prevention drug, dose, duration, warning signs, and after-hours contact. Also ask for the surgeon’s annual primary and revision volumes, the hospital’s infection, readmission, and revision rates, and the referral plan for bone loss or infection if revision surgery is needed.
Compare Surgeons Using Their Results and Care Systems
A confident recommendation is not proof of better results. If two surgeons disagree, ask each to state the diagnosis, proposed operation, expected benefit, and reason the alternative is unsuitable; then compare their evidence rather than their implant brand or promotional claims.
| Evidence to compare | What to request | What it does not prove |
|---|---|---|
| Surgeon credentials and surgeon annual volume | Board certification, knee-specific training, and personal yearly numbers for primary and revision replacements | Certification does not establish superior outcomes |
| Hospital performance | Hospital infection and readmission rates, revision rate, emergency-transfer plan, and registry participation | Hospital figures do not equal that surgeon’s risk-adjusted results |
| Recovery and safety system | Written pain-control, early-mobility, and blood-clot prevention plans, including drug, dose, duration, warning signs, and post-discharge contact | A standard pathway may not suit your clot or bleeding risk |
| Follow-up evidence | Patient-reported outcomes, complication definitions, follow-up period, and results for patients resembling you | A testimonial or headline success rate is not a comparable dataset |
Ask whether figures cover the last three to five years and separate primary from revision surgery. Compare like with like: age, obesity, diabetes, deformity, previous operations, and case complexity can shift outcomes. Medicare Care Compare can provide hospital-level measures in the United States, but it cannot replace surgeon-specific data.
At UR Orthopaedic Clinic, take both recommendations, imaging, and written outcome figures to the consultation; the useful answer is a reasoned plan, not a promise. A surgeon who does not perform revisions should name a specific referral pathway for infection, bone loss, or implant failure.
Related service
Total Knee Replacement At our orthopaedic clinic, we provide advanced Total Knee Replacement surgery for patients suffering from severe knee arthritis, joint deformity, or... View service → |
Frequently asked questions
How do I know whether knee replacement surgery is the right next step?
Consider surgery when diagnosed arthritis still causes substantial pain or stiffness after a well-run non-surgical plan and limits walking, stairs, sleep, work, or personal care. Worsening deformity, pain at rest, or rapidly declining function warrants assessment.
How does a surgeon confirm that I am suitable for knee replacement?
The surgeon should assess your symptoms, walking and knee function, physical examination findings, medical history, and imaging before recommending surgery.
Should I choose a surgeon based on a specific knee replacement technique or implant?
Match the surgeon’s expertise to the operation you may need, then ask why a technique and implant fit your anatomy, activity goals, risks, and expected recovery.
What should I compare between knee replacement surgeons?
Compare relevant surgical experience, patient results, complication discussions, rehabilitation arrangements, communication, and the system for follow-up after surgery.